The short answer
Back pain returns because the tissue never regained the capacity it lost, not because your spine is fragile. Rest settles the episode and leaves you weaker than before, so the next ordinary load starts it again. Loading the tissue back to tolerance is what breaks the cycle.
- Recurring back pain is a pattern of load and lost capacity, not a fragile spine.
- Rest resolves the flare and leaves the cause untouched.
- Stiff hips and a stiff mid-back push load into a few lumbar segments.
- Leg symptoms change the plan; red flag symptoms need a physician, not therapy.
Almost every person who calls me about their back has done this at least twice before. They know the routine: a few bad days, some rest, maybe some anti-inflammatories, and it settles. Then four months later it happens again, from something as trivial as picking up a sock.
That pattern is not bad luck and it is not a fragile spine. It is information.
Rest treats the flare, not the cause
When your back goes, two things are happening. There is genuinely irritated tissue, and there is a nervous system that has responded by cranking up muscle guarding around the area. Rest and time reliably calm both. That is why it always seems to get better on its own.
What rest does not do is change the movement pattern that loaded the tissue in the first place, or restore the capacity you lost while you were being careful. So you return to normal life with the same pattern and slightly less tolerance than you had before. The math of that only goes one way.
Pain does not simply show up with age. It is the result of injuries, muscle and skeletal misuse over time. Movement caused the pain to appear, and correct movement and coaching can help it go away.
The three things I look for
Where the load is going. Most recurring back pain concentrates load in one narrow zone — often a couple of lumbar segments doing the work that stiff hips and a stiff mid-back have stopped contributing. Those segments are not damaged. They are overworked.
What the hips and thoracic spine are doing. If your hips do not extend and your mid-back does not rotate, your lower back does both jobs on every step, every lift and every golf swing. Free those up and the load spreads.
How much your back can actually tolerate. Capacity is measurable. A back that fails at a suitcase is a back with a capacity problem, and capacity problems have a well-understood solution.
Sciatica is a separate question
If pain, numbness or weakness travels down the leg, the conversation changes. That is nerve root irritation, and where the irritation comes from — a disc, a facet joint, or the muscle the nerve passes beneath — completely changes the treatment.
Neurological testing is part of the examination for exactly this reason. And so is the possibility that the answer is not therapy at all: loss of bladder or bowel control, numbness in the saddle region, or progressive leg weakness are urgent medical problems, not appointments to book next week. Knowing when to send you elsewhere is part of the differential diagnosis training in the Diploma in Osteopractic, and I use it.
What I do about it in a session
Spinal manipulation to restore movement at the segments that have stopped contributing, because a stiff joint keeps the muscles around it guarding.
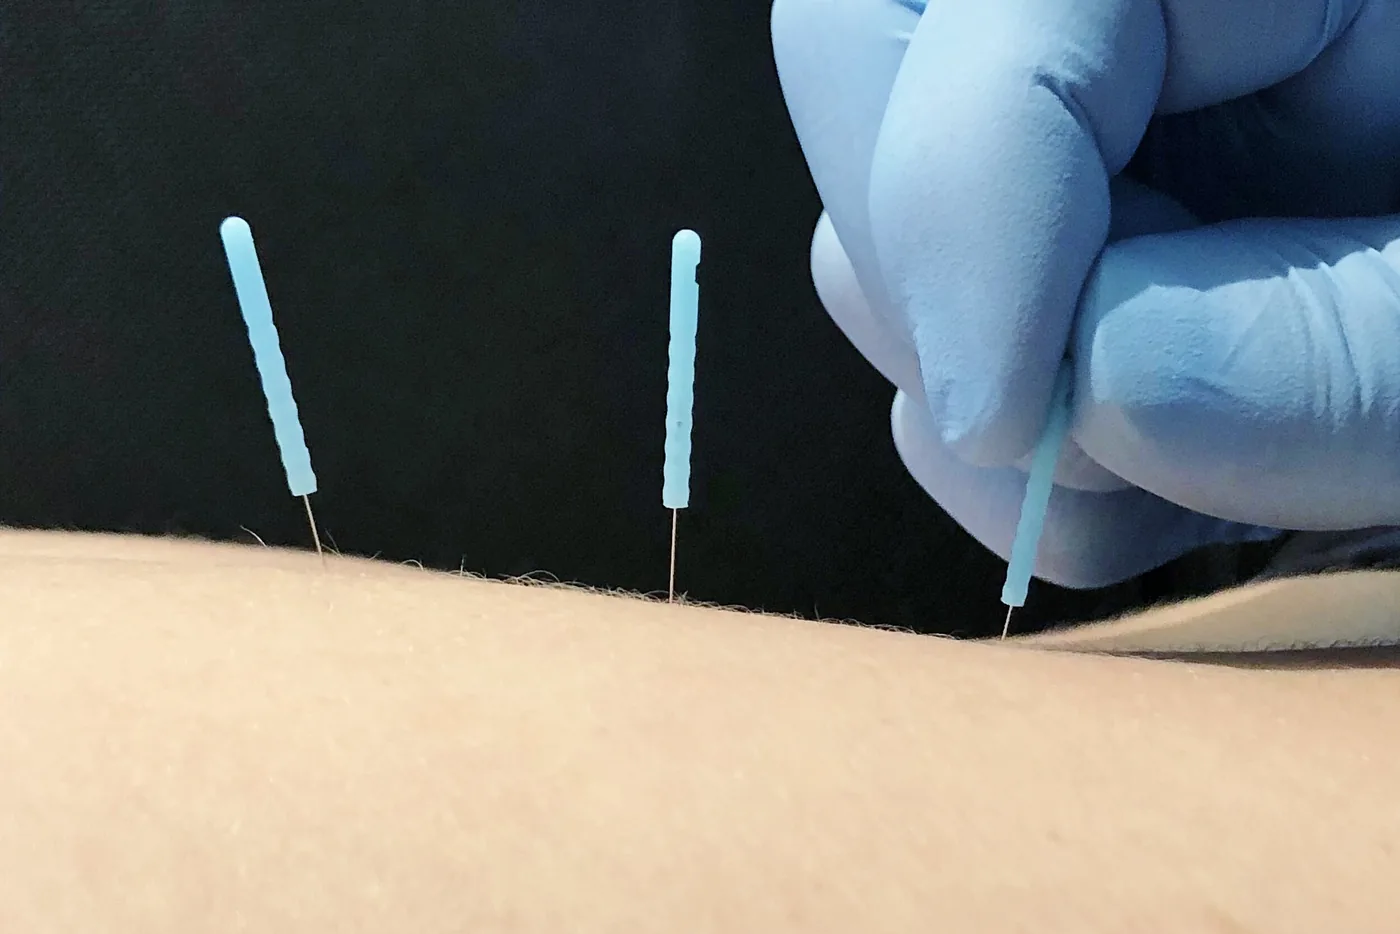
Dry needling or cupping where the surrounding tissue is genuinely restricted — the quadratus lumborum and glutes are common offenders and both refer pain in patterns that convincingly imitate other problems.
Then loading. Every single time. The range you gained in the first forty minutes has to be used under load in the same session, or the nervous system has no reason to keep it.
Sitting, driving and the working week
Prolonged sitting is not damaging and it is a sustained load, and the distinction matters because one of those framings makes people afraid of chairs.
What produces symptoms is duration in any single position. Standing up every twenty to thirty minutes does more than any adjustment to the chair.
Long drives are the harder version, because you cannot get up. Adjusting the seat before a long journey, and stopping every hour or so, is worth the few minutes it costs.
A standing desk helps by making change easy rather than because standing is superior. Standing all day produces its own set of complaints.
What a proper assessment measures
Which movements reproduce the symptom and which relieve it, tested in each direction rather than assumed from where it hurts.
Hip mobility and thoracic mobility, because a lumbar spine surrounded by stiffness takes range it was not built for.
Trunk endurance, tested rather than eyeballed, so there is a number to compare against in six weeks.
And a neurological screen if there is anything at all in the leg. That takes three minutes and it decides whether the plan needs to change.
What a flare looks like and what to do in the first week
Severe, often sudden, frequently on a morning after an unremarkable day. Movement is guarded, sitting is worse than walking for most people, and the first hour of the day is the hardest.
Keep moving within comfort, in small amounts and often. Walking is well tolerated by almost every acute back and it is the single most useful thing available in week one.
Heat rather than ice for most people, because the limitation is largely muscular guarding.
Avoid two things: total rest, which prolongs it, and testing the back repeatedly to see how bad it is, which is a load on already irritable tissue and produces no useful information.
What the imaging usually shows, and why it rarely helps
Disc bulges, degenerative change and facet arthrosis turn up on scans of enormous numbers of people with no back pain at all, and the rates rise steadily with age. A report describing several of those findings is frequently describing a spine of your age rather than the source of your symptoms.
That is why guidelines discourage routine imaging for ordinary back pain. It does not change the treatment, and it reliably changes how people feel about their own spine.
Imaging earns its place when something in the history or examination points beyond a mechanical problem, or when a decision genuinely depends on the result.
If you already have a scan, bring the report. It is one piece of information among several, and the examination is what connects it to what you are actually feeling.
The load story behind most recurrences
Almost every episode I see followed a change: a house move, a training block, a new job, a period of poor sleep, two weeks of unusual driving.
The back did not fail. The demand went up faster than the capacity, which is the same mechanism behind most tendon and bone problems.
Knowing that changes what you do about it. The question is not what is wrong with your spine but what changed in the six weeks before it started, and that answer usually arrives within two minutes of asking.
It also tells you what to protect during the next busy period, which is the part that actually reduces recurrences.
Why the fear matters as much as the mechanics
Beliefs about the back predict disability better than most physical findings do. People who believe their spine is damaged move less, guard more and recover more slowly, and that effect is measurable rather than a figure of speech.
Decades of being told to protect the back, lift a certain way and avoid bending have left a great many people convinced that ordinary movement is dangerous.
So part of the treatment is accurate information, delivered plainly: backs are robust, bending is not damage, and pain during movement is not a report of harm.
That conversation is not a consolation prize offered when nothing else worked. It is one of the more effective things available.
Why the plan has an end point
The typical client here is seen one to two visits a week, and the plan runs until the result holds on its own. That is not a marketing position; it is what happens when a full hour of one-on-one time is spent on assessment, treatment and coaching rather than split across three people on a gym floor.
Every client is educated with therapeutic exercise and self-mobilization techniques so you can treat yourself at home. The goal is a back you can manage, not a standing appointment.
And the honest version: if your back is going to hold, it holds because of what you do in the six days between visits. My job is to make those six days count.
What to do this week
- Stop testing it. Repeatedly bending forward to check whether it still hurts keeps the area sensitized.
- Keep moving within tolerance. Walking is almost always tolerated and almost always helps.
- Change position often. It is not the sitting, it is the not-moving.
- Note what genuinely aggravates it, with times. That list is the most useful thing you can bring to a first appointment.